Lower Back Pain & Sciatica: Clinician-Led Self-Tests in Sweden
Lower back pain is the leading cause of activity limitation globally. If you experience severe lower back pain in Sweden, you may be unsure where to seek care. Understanding whether symptoms represent benign mechanical lumbago or radicular disc herniation is essential for securing appropriate care.
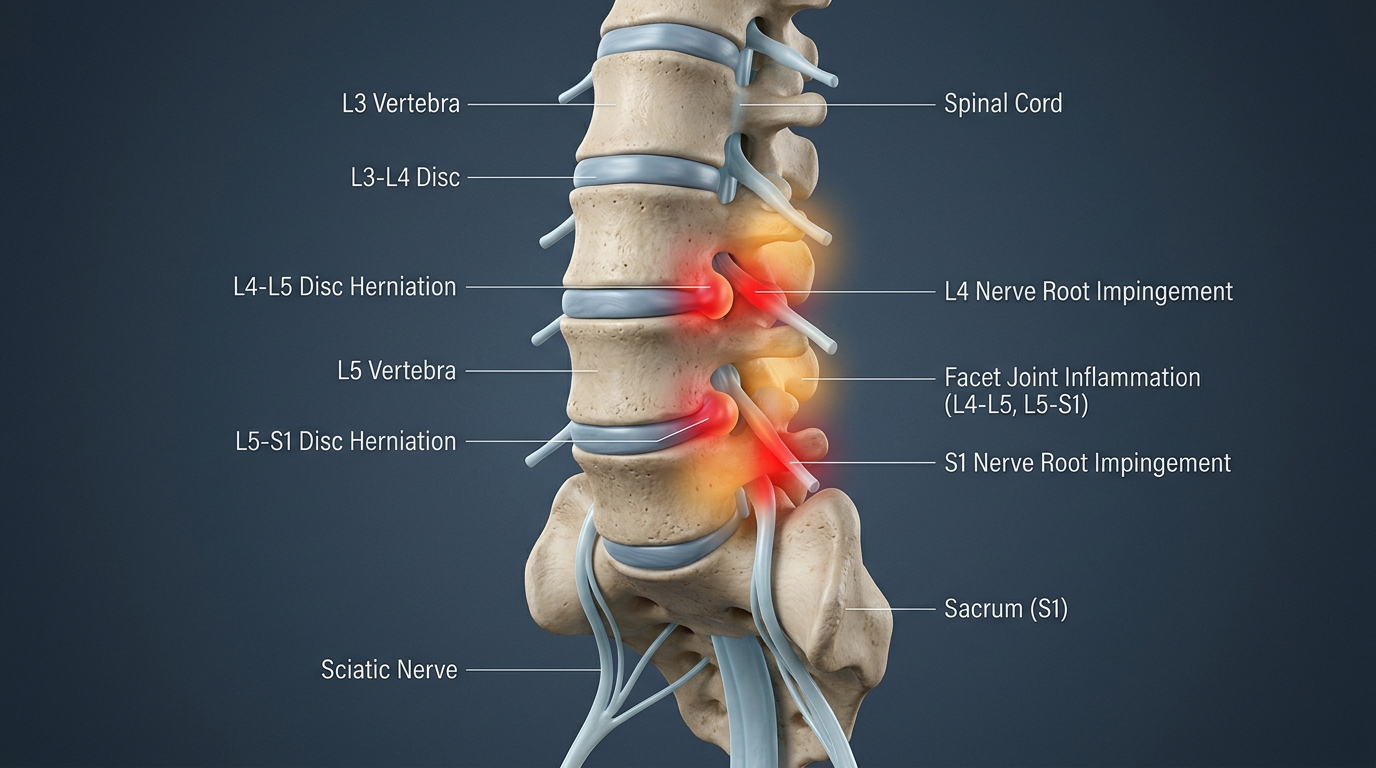
Symptom Classification: Mechanical Back Pain vs True Sciatica
Clinicians classify back symptoms primarily by anatomical radiation:
- Axial Lumbago (Local Back Pain): Pain confined to the lumbar spine and gluteal region. Almost always muscular guarding, ligamentous strain, or facet joint irritation. Highly responsive to early movement.
- Radiculopathy (True Sciatica): Sharp, lancinating, or burning pain traveling below the knee into the calf, ankle, or toes. Often caused by an intervertebral disc herniation compressing a specific spinal nerve root (L4, L5, or S1).
- Neurogenic Claudication: Bilateral leg heaviness, numbness, or cramping triggered by upright walking and relieved by leaning forward (classic for lumbar spinal stenosis in patients aged 60+).
Three Clinician-Guided Self-Tests
Perform these movements gently on a level surface. Discontinue immediately if sharp radiating pain intensifies.
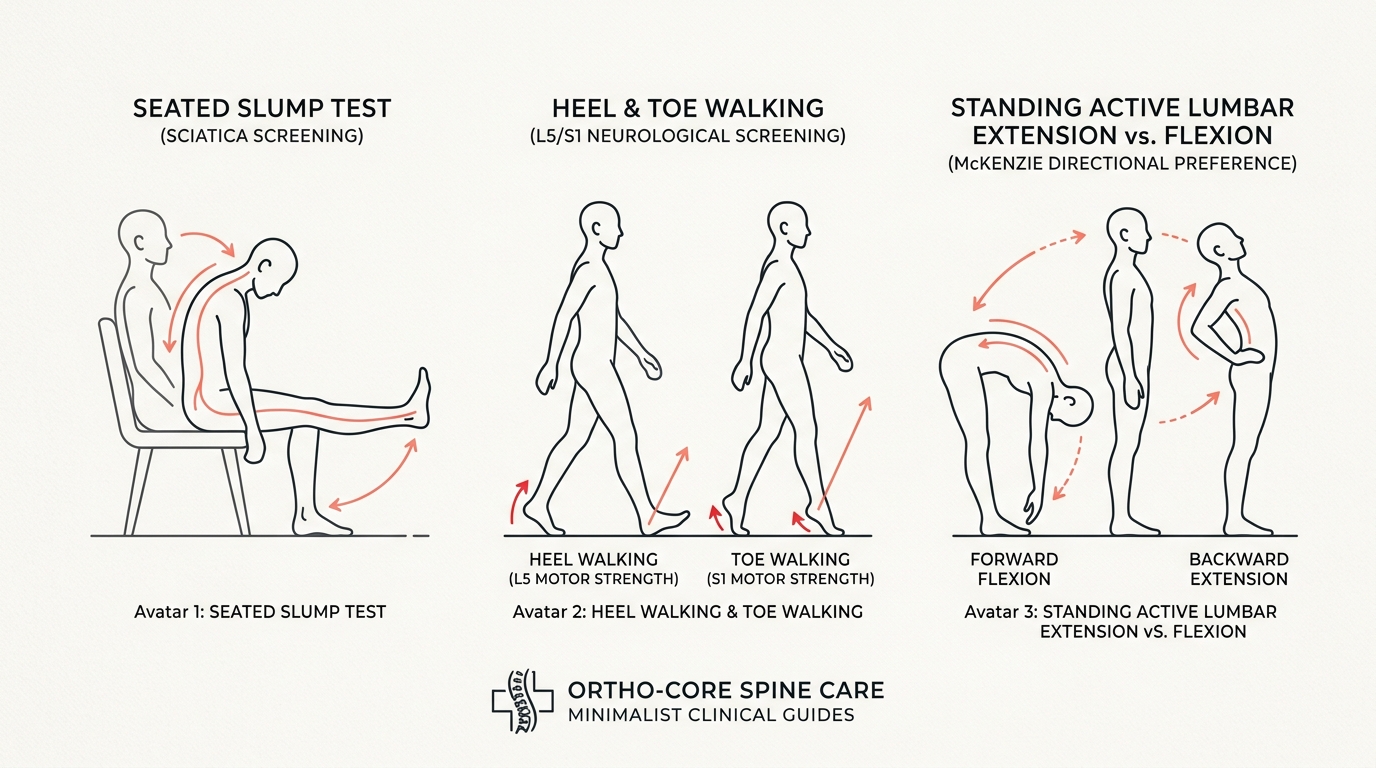
Test 1: Seated Slump Test (Sciatic Nerve Dural Tension)
Procedure: Sit on a firm chair with hands clasped behind your back. Slump your entire spine forward, then flex your neck until your chin touches your chest. Slowly straighten the affected leg out in front of you, and dorsiflex your foot/toes upward toward your face.
Positive Finding: A sharp, pulling sensation radiating down the posterior thigh, past the knee into the calf/foot that immediately alleviates when you raise your head confirms neurodynamic irritation consistent with lumbar disc radiculopathy.
Test 2: Heel & Toe Walking Test (L5 & S1 Motor Strength)
Procedure: Walk 10 steps forward bearing weight solely on your heels (toes elevated). Turn around and walk 10 steps solely on your tiptoes with heels elevated.
Positive Finding: Inability to walk on your heels (foot drop) indicates L5 nerve root weakness. Inability to elevate your heel on one side indicates S1 nerve root weakness.
Test 3: McKenzie Directional Preference (Extension vs Flexion)
Procedure: Stand with feet shoulder-width apart and hands supported against your lower back. Perform 5–10 slow, controlled backward bends (extensions). Note the pain pattern, then perform gentle forward bends.
Positive Finding: If backward bending causes the radiating leg pain to retreat upward toward the spinal midline ("centralization"), this indicates a posterior disc herniation with strong mechanical healing potential.
Differential Diagnosis Matrix
| Condition | Pain Distribution | Aggravating Factor | Relieving Factor | Recommended Action |
|---|---|---|---|---|
| Acute Lumbago | Localized lower back and buttocks. | Sudden twists, prolonged sitting. | Gentle walking, heat, gradual movement. | Physiotherapy within 48 hours. |
| Lumbar Disc Herniation | Shooting pain past knee into foot, tingling. | Sitting, coughing, sneezing, forward flexion. | Lying flat with knees supported, walking. | Lumbar MRI if weakness or symptoms persist >4 weeks. |
| Lumbar Spinal Stenosis | Bilateral leg tiredness, cramping during walking. | Walking uphill, standing upright. | Sitting, leaning forward on shopping cart. | Lumbar MRI to evaluate spinal canal diameter. |
| Facet Joint Arthropathy | Bilateral back stiffness, morning ache. | Backward extension and rotation. | Gentle forward flexion, rest. | Core stabilization and posture rehab. |
⚠️ Red Flags – Immediate Emergency Symptoms
Seek immediate hospital emergency care (call 112 in Sweden) if you develop:
- Cauda Equina Syndrome: Numbness in the groin/perineal area ("saddle anesthesia"), acute loss of bladder or bowel control, or urinary retention.
- Progressive Motor Loss: Sudden foot drop or buckling knees when walking.
- Systemic Signs: Constant night pain accompanied by unexplained weight loss or fever.
When to Pursue a Private Lumbar MRI in Sweden
Under Swedish public primary healthcare guidelines, MRI imaging is generally reserved for patients experiencing persistent pain beyond 6 to 12 weeks. When nerve symptoms cause severe functional disruption, a private Lumbar Spine MRI provides critical diagnostic certainty within days:
- Identifies the precise disc level (L4-L5 vs L5-S1) and whether sequestration or extrusion has occurred.
- Evaluates the exact degree of thecal sac and exit foramen impingement.
- Informs decisions regarding selective nerve root injections or minimally invasive microdiscectomy.
Book a Spine Specialist Assessment & Rapid MRI in Sweden
Consult with a licensed orthopedic physiotherapist via video within 24 hours (SEK 690), or secure our comprehensive spine investigation package with guaranteed private MRI within 10 days (SEK 9,900).
Book Spine Pathway at Vård.se →